
{"cover":"Professional landscape format (1536×1024) editorial hero image with SHORT bold text overlay: 'Estrogen and Muscle Building After 40' in bold white sans-serif on a deep teal semi-transparent panel, centered, 8% safe margins, two balanced lines, no character near the edge. Background: bright, naturally lit gym photograph of a confident woman in her late forties mid-deadlift with a loaded barbell, chalk dust in the air, another woman around 55 spotting her in the soft-focus background, large windows with daylight, warm wood platform, teal and warm amber color grade, high-contrast magazine-cover polish. No price tables, no numbers grids.","content":["Landscape 1536×1024 annotated mechanism diagram titled visually around estrogen's role in tissue: center shows a stylized female silhouette in mid-squat, with thin callout lines pointing to four labelled targets, 'Muscle fiber repair', 'Tendon stiffness', 'Bone density', 'Recovery signaling'. Side panel shows a simple descending estrogen curve across three labelled life stages: 'Pre-40', 'Perimenopause', 'Postmenopause'. Clean white background, navy-and-coral palette, crisp medical-guide illustration style, labels 1-4 words, sharp, non-overlapping, inside 5% safe margin.","content2":"","2":"Landscape 1536×1024 numbered four-step weekly training flow card for menopausal strength programming: Step 1 'Warm-up and mobility' with an illustrated hip-opener figure, Step 2 'Heavy compound lifts' with a squat rack icon, Step 3 'Impact work' with a figure mid-hop, Step 4 'Recovery and sleep' with a moon-and-pillow icon. Horizontal timeline ribbon connecting steps, soft sage green and charcoal palette, flat vector infographic with subtle shadows, short labels only, inside 5% safe margin.","3":"Landscape 1536×1024 bright studio flat-lay documentary photo of a menopause muscle-building nutrition setup on a pale stone countertop: grilled salmon portion, Greek yogurt bowl, cottage cheese, lentils, a scoop of whey powder in a shaker, creatine tub, vitamin D capsules, and a tape measure, with four thin callout labels reading 'Protein per meal', 'Creatine monohydrate', 'Vitamin D', 'Calcium sources'. Overhead angle, crisp daylight, warm neutral palette with one coral accent, sharp food-magazine photography, labels inside 5% safe margin."}}

Last updated: October 20, 2026
Quick Answer
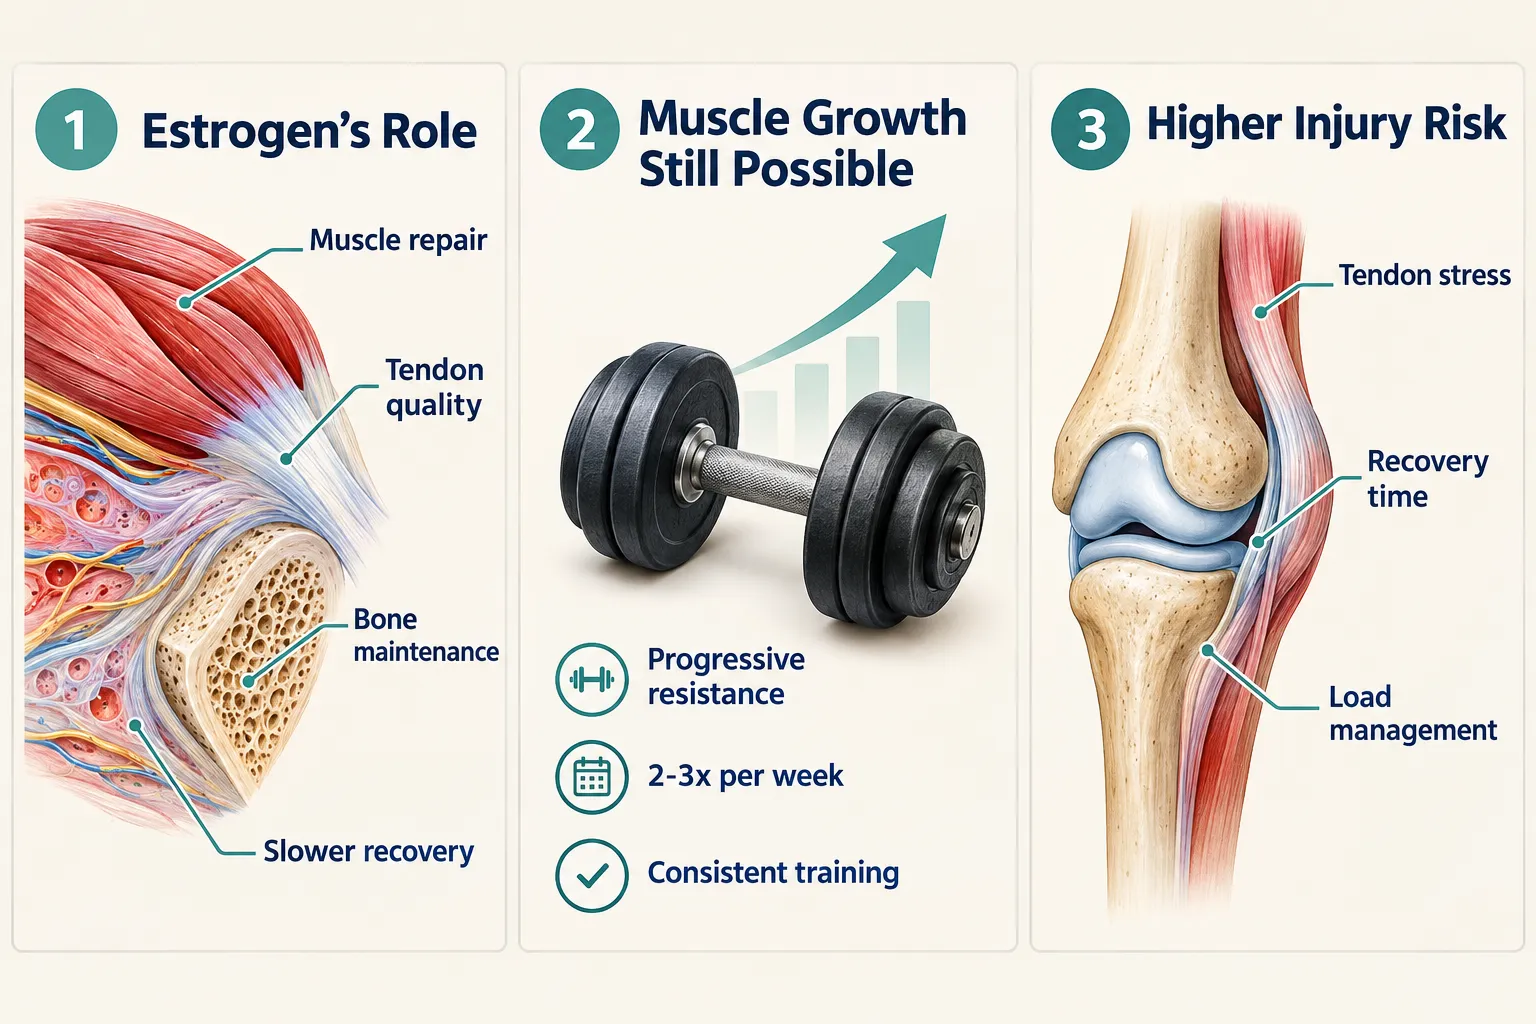
Estrogen and muscle building after 40 are closely linked: as estrogen falls through perimenopause and menopause, muscle repair, tendon resilience, and bone density all take a hit, which is why strength training has to change. But menopause does not block muscle growth. Progressive resistance training two to three times a week, heavier loads over time, enough protein, and added impact work still produce real gains in muscle and strength [1][2]. The conditions are harder, not impossible.
Key Takeaways
- Estrogen supports muscle repair, connective tissue quality, and bone maintenance, so its decline makes recovery slower and injury risk higher.
- Women can and do gain muscle during and after menopause with progressive overload [1][2].
- The core prescription is resistance training 2-3 times per week, with loads that get heavier over months.
- Add impact exercise (hops, jumps, brisk stair work) to protect bone alongside strength work [3].
- Protein, calcium, and vitamin D matter more after 40 than before it.
- Hormone therapy shows modest and often nonsignificant effects on muscle mass; it's not a muscle-building drug [4].
- Creatine monohydrate and vitamin D are the supplements with the most credible support.
- Muscle loss is largely reversible with training, though not always back to a 30-year-old baseline.
- Men lose muscle too, but more slowly and without the sharp hormonal drop-off.
- Expect strength gains in 4-6 weeks and visible shape change in 3-6 months.
What does estrogen do for muscle growth and strength?
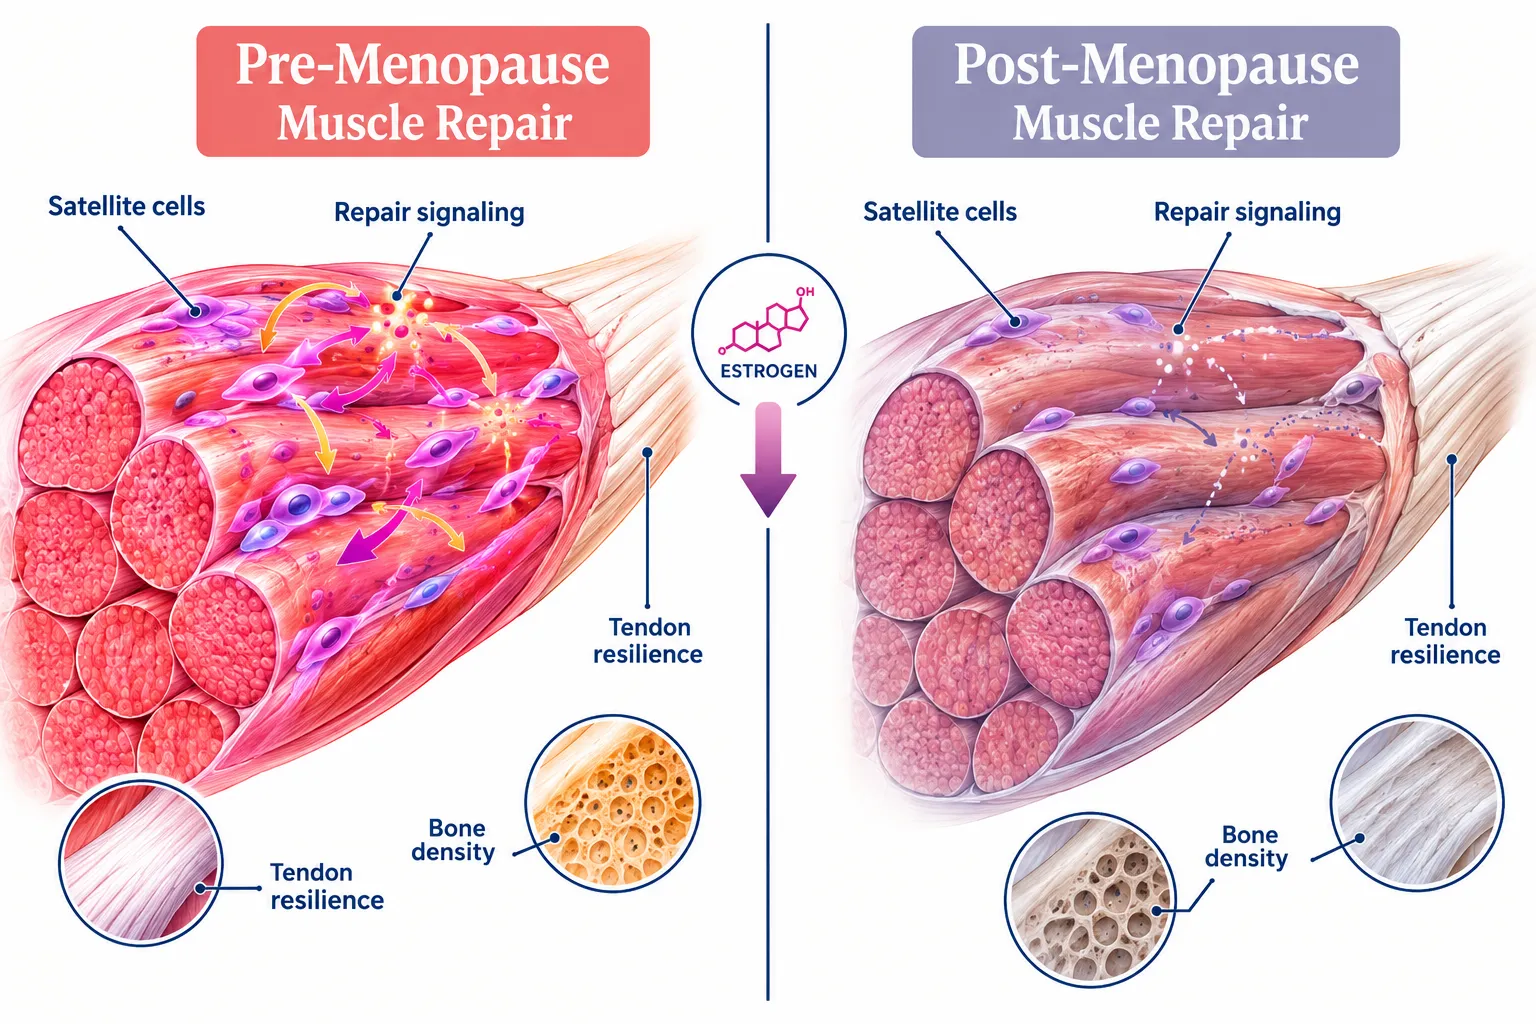
Estrogen acts as a protective, repair-supporting hormone for muscle, tendon, and bone. When it drops, the tissue still works, it just repairs more slowly and tolerates less abuse.
)
What estrogen influences:
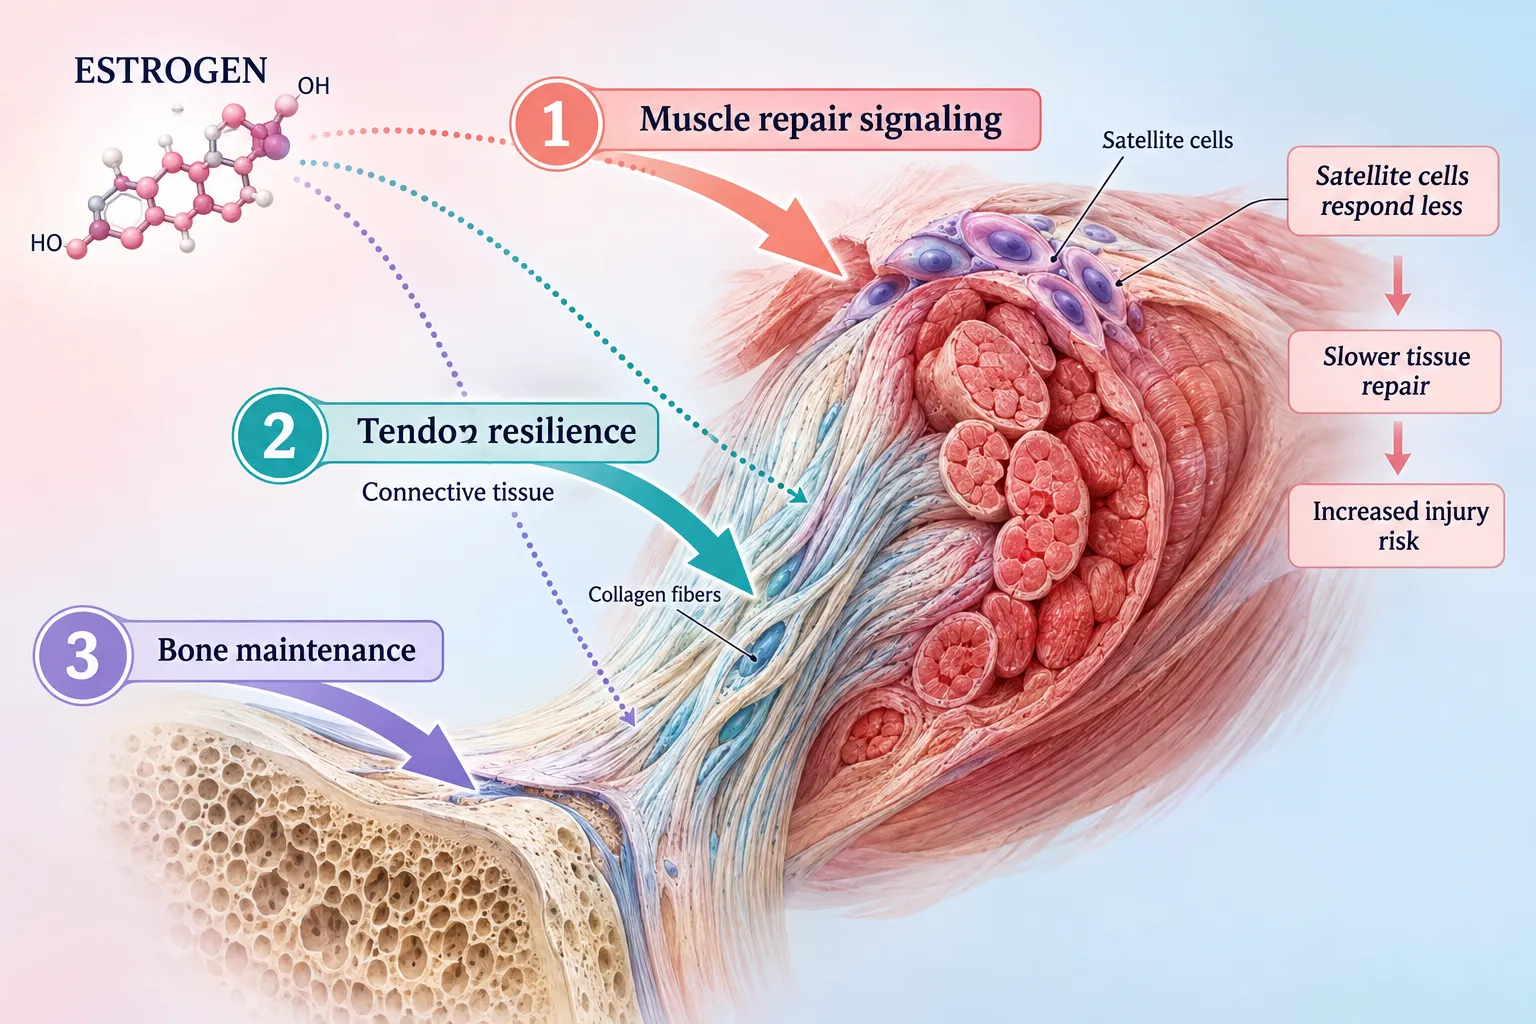
- Muscle repair signaling. Satellite cells (the repair crew inside muscle) respond less efficiently when estrogen is low, so soreness lingers longer.
- Connective tissue. Tendons and ligaments lose some elasticity and stiffness regulation, which is part of why nagging shoulder, hip, and Achilles complaints spike in the forties and fifties.
- Bone turnover. Estrogen restrains bone breakdown. Its decline speeds bone loss, making impact and loading work a priority, not an extra [3].
- Inflammation and recovery. Lower estrogen is associated with a more inflammatory baseline, which eats into recovery capacity.
Practical read: treat the warm-up and recovery days as part of the program, not as optional extras.
How much muscle do women lose during perimenopause, and is it permanent?
Lean mass declines measurably across the menopause transition, and the drop is linked to falling estrogen rather than age alone [4][5]. The loss is largely reversible with consistent resistance training, though recovering every gram isn't guaranteed.
Two things happen at once: gradual age-related muscle loss (sarcopenia) and an estrogen-driven acceleration during the transition years. Training addresses both. Untrained women who start lifting in their fifties routinely regain strength and lean mass [2].
Decision rule: if you're in perimenopause and have never lifted seriously, start now rather than waiting for symptoms to settle. The transition years are when loading pays the biggest dividend.
Why is it harder to build muscle after 40 for women?
It's harder because the same workout produces a smaller repair response, recovery takes longer, and sleep and stress, both commonly disrupted in perimenopause, are now limiting factors.
The main friction points:
- Blunted response to protein. Older muscle needs a larger protein dose per meal to trigger the same building signal.
- Slower recovery. 48 hours between hard sessions for the same muscle group becomes the floor, not the ceiling.
- Poor sleep. Hot flashes and night waking cut into the window when repair actually happens.
- Lower baseline activity. Joint pain quietly reduces daily movement, which reduces stimulus.
- Under-loading. Many women train with weights far too light to signal growth.
Edge case: women on aromatase inhibitors after breast cancer experience a sharper hormonal drop and often more joint pain. Training still helps, but progression should be slower and medically supervised.
What's the best strength training routine for menopausal women?
The best routine is full-body progressive resistance training two to three times weekly, built on compound lifts, with heavy-ish loads and added impact work for bone [1][3][6].
)
A workable weekly template:
| Day | Focus | Example |
|---|---|---|
| Mon | Full-body strength | Squat, row, press, hip hinge |
| Tue | Walk + mobility | 30-40 min walk, hip/thoracic work |
| Wed | Impact + core | 2 sets of 10 hops per leg, carries, planks |
| Thu | Rest or easy movement | , |
| Fri | Full-body strength | Deadlift, lunge, pull-down, overhead press |
| Sat | Optional third lift or cardio | Intervals or light session |
| Sun | Rest | , |
Loading guidance: 2-4 sets of 5-10 reps on main lifts, stopping 1-2 reps short of failure. Add weight when you can complete the top of the rep range with good form on all sets.
Always include a 10-minute warm-up: general movement, then hip and shoulder mobility, then lighter sets of the first lift. After 40, skipping this reliably costs training days.
How often should women over 40 lift weights?
Two to three sessions a week is the evidence-backed target, and three is better if recovery allows [1][6]. More than four hard sessions rarely helps and often backfires when sleep is already compromised.
- Two days: full-body both days. Minimum effective dose.
- Three days: full-body, or upper/lower/full split.
- Four+ days: only with excellent sleep and at least one genuinely easy day.
Common mistake: swapping strength sessions for more cardio when the scale stalls. Cardio helps the heart; it doesn't defend muscle or bone the way loaded lifting does.
Does hormone replacement therapy help you build muscle?
Hormone therapy has modest and often statistically nonsignificant effects on muscle mass, so it should not be treated as a muscle-building intervention [4]. It may support bone density, symptom relief, and better sleep, which can indirectly improve training quality.
Choose HRT based on symptoms, bone health, and medical history in discussion with a clinician, not on hopes of hypertrophy. Women on HRT still need the same progressive overload as women who aren't. Training does the muscle work; hormone therapy, where appropriate, removes some of the obstacles.
How much protein do I need during menopause to build muscle?
Most active women in perimenopause and menopause do well at roughly 1.2-1.6 g of protein per kg of body weight daily, spread across three or four meals with 25-40 g each. That's higher than general adult guidelines because older muscle responds less to small doses.
)
Also non-negotiable:
- Calcium: from dairy, fortified plant milks, tinned fish with bones, leafy greens.
- Vitamin D: commonly supplemented, especially in low-sunlight climates, get levels checked.
- Total calories: chronic under-eating is the fastest route to losing muscle while training hard.
Quick example: a 68 kg woman aims for about 82-109 g protein daily, Greek yogurt at breakfast, chicken or lentils at lunch, fish or tofu at dinner, with a shake if a meal falls short.
What supplements actually work for muscle building in menopause?
Only a short list has credible support: creatine monohydrate, vitamin D (if deficient), protein powder as a convenience tool, and calcium if dietary intake is low.
- Creatine monohydrate, 3-5 g daily, no loading needed. Supports strength and training output.
- Vitamin D, dose based on blood levels and clinician advice.
- Protein powder, food first, powder to close gaps.
- Skip: testosterone boosters, collagen marketed as a muscle builder, "menopause fat burners."
Decision rule: if a supplement promises to fix hormones, treat the claim as marketing.
Why do I keep losing muscle even though I work out?
Usually one of four things: the weights are too light, protein is too low, calories are too low, or recovery is too poor. Showing up isn't the same as progressively overloading.
Troubleshooting checklist:
- Have your working weights increased in the last eight weeks? If not, that's the problem.
- Are you hitting 25-40 g protein at most meals?
- Are you eating enough overall, or dieting hard while training hard?
- Are you sleeping under six hours most nights?
- Are you doing mostly classes and cardio with light dumbbells?
- Any untreated thyroid issue, medication change, or illness?
Fix in that order. Load and protein solve the majority of cases.
Do men deal with the same muscle loss issue after 40?
Men also lose muscle with age, but the decline is slower and steadier because testosterone falls gradually rather than dropping sharply the way estrogen does during menopause [5]. Men rarely face a two-to-four-year window of accelerated loss.
The training answer is nearly identical, progressive resistance work, adequate protein, but women in the transition need more attention to bone loading, connective tissue care, and recovery management.
Common mistakes women make when strength training after 40
The biggest mistake is training too light for too long. The others are skipping the warm-up, chasing sweat instead of strength, and under-eating.
- Using 3 kg dumbbells for years and expecting change.
- Jumping into heavy loading with no technique base (medical clearance and conservative progression matter more once estrogen falls).
- Treating soreness as the goal.
- Ignoring bone: no impact, no jumping, no loaded carries.
- Program-hopping every three weeks, so overload never accumulates.
- Cutting calories hard while adding training volume.
How long does it take to see muscle gains during menopause?
Expect noticeable strength gains in 4-6 weeks (largely neural), visible changes in muscle shape around 3-6 months, and meaningful bone density change only after 12 months or more of consistent loading.
Track lifted weight, reps, and how daily tasks feel rather than scale weight. Muscle gained alongside fat lost can leave the scale flat while clothes and strength both change.
FAQ
Can you still gain muscle mass during menopause?
Yes. Progressive resistance training builds muscle in perimenopausal and postmenopausal women; the rate is slower than at 25, but the direction is the same [1][2].
Does estrogen loss cause weight gain?
The transition is linked to body composition shifts, especially more abdominal fat and less lean mass. Strength training and adequate protein counter the muscle side directly.
Should I lift heavy or do high reps?
Mostly heavier loads in the 5-10 rep range, taken close but not to failure. Light high-rep work alone under-stimulates muscle and bone.
Is walking enough to protect muscle?
No. Walking helps heart health and mood but provides too little load to maintain muscle or bone. Pair it with resistance training.
Do I need to train around my cycle in perimenopause?
Cycles become irregular, so rigid cycle-based plans often fail. Adjust by how you feel each week instead: push loads on good weeks, reduce volume on bad-sleep weeks.
Is it safe to lift weights with osteopenia or osteoporosis?
Often yes, with clinician clearance and coaching. Loaded strength work is protective, but heavy spinal flexion and high-impact jumping may need modification.
How long should rest between sets be?
Two to three minutes on heavy compound lifts. Short rests limit the load you can lift, which limits the stimulus.
Will lifting make me bulky?
No. With low estrogen and no testosterone surge, women add muscle slowly. The realistic outcome is denser, stronger, leaner.
Conclusion
Lower estrogen changes the terms of strength training after 40, slower repair, touchier tendons, faster bone loss, but it doesn't remove the ability to build muscle. What changes is how deliberate the plan needs to be.
Next steps:
- Book medical clearance if you have joint issues, bone density concerns, or cardiac history.
- Schedule two to three full-body strength sessions this week and protect them.
- Pick five compound lifts and log weight and reps every session.
- Raise protein to 25-40 g per meal starting tomorrow.
- Add 10 minutes of warm-up and mobility before every lift.
- Add two short impact sets weekly for bone.
- Reassess at 12 weeks using logged loads, not the scale.
References
- Menopause Perimenopause Exercise Strength Training. apnews.com.
- Build Muscle After Menopause. hingehealth.com.
- Importance of Movement Through Menopause with Vail Healthspan. vailhealth.org.
- Full. frontiersin.org.
- Jcsm.70232. onlinelibrary.wiley.com.
- Strength Training Perimenopause. everydayhealth.com.